Get your free personalized podcast brief
We scan new podcasts and send you the top 5 insights daily.
For DLBCL patients awaiting CAR-T cell therapy, particularly those with aggressive disease, bispecific antibodies are the preferred bridging strategy. This approach effectively controls disease and reduces tumor burden for better CAR-T outcomes, while avoiding the T-cell depleting effects of traditional chemotherapy.

Related Insights
Moving CAR T-cell therapy to earlier treatment lines is crucial. This approach targets cancer before it develops resistance and, more importantly, utilizes patient T-cells that are healthier and more effective, not having been damaged by extensive prior chemotherapy regimens.

An exploratory strategy for DLBCL patients involves using ctDNA to detect minimal residual disease after CAR T-cell therapy. This allows for early intervention with bispecific antibodies when the disease burden is low, potentially preventing full clinical progression, a shift from reactive to proactive treatment.

In follicular lymphoma, the treatment goal is durable remission with manageable toxicity, not necessarily a cure. Therefore, clinicians frequently prefer using a bispecific antibody first, reserving the more complex and toxic CAR-T cell therapy for transformed disease or after a bispecific fails.
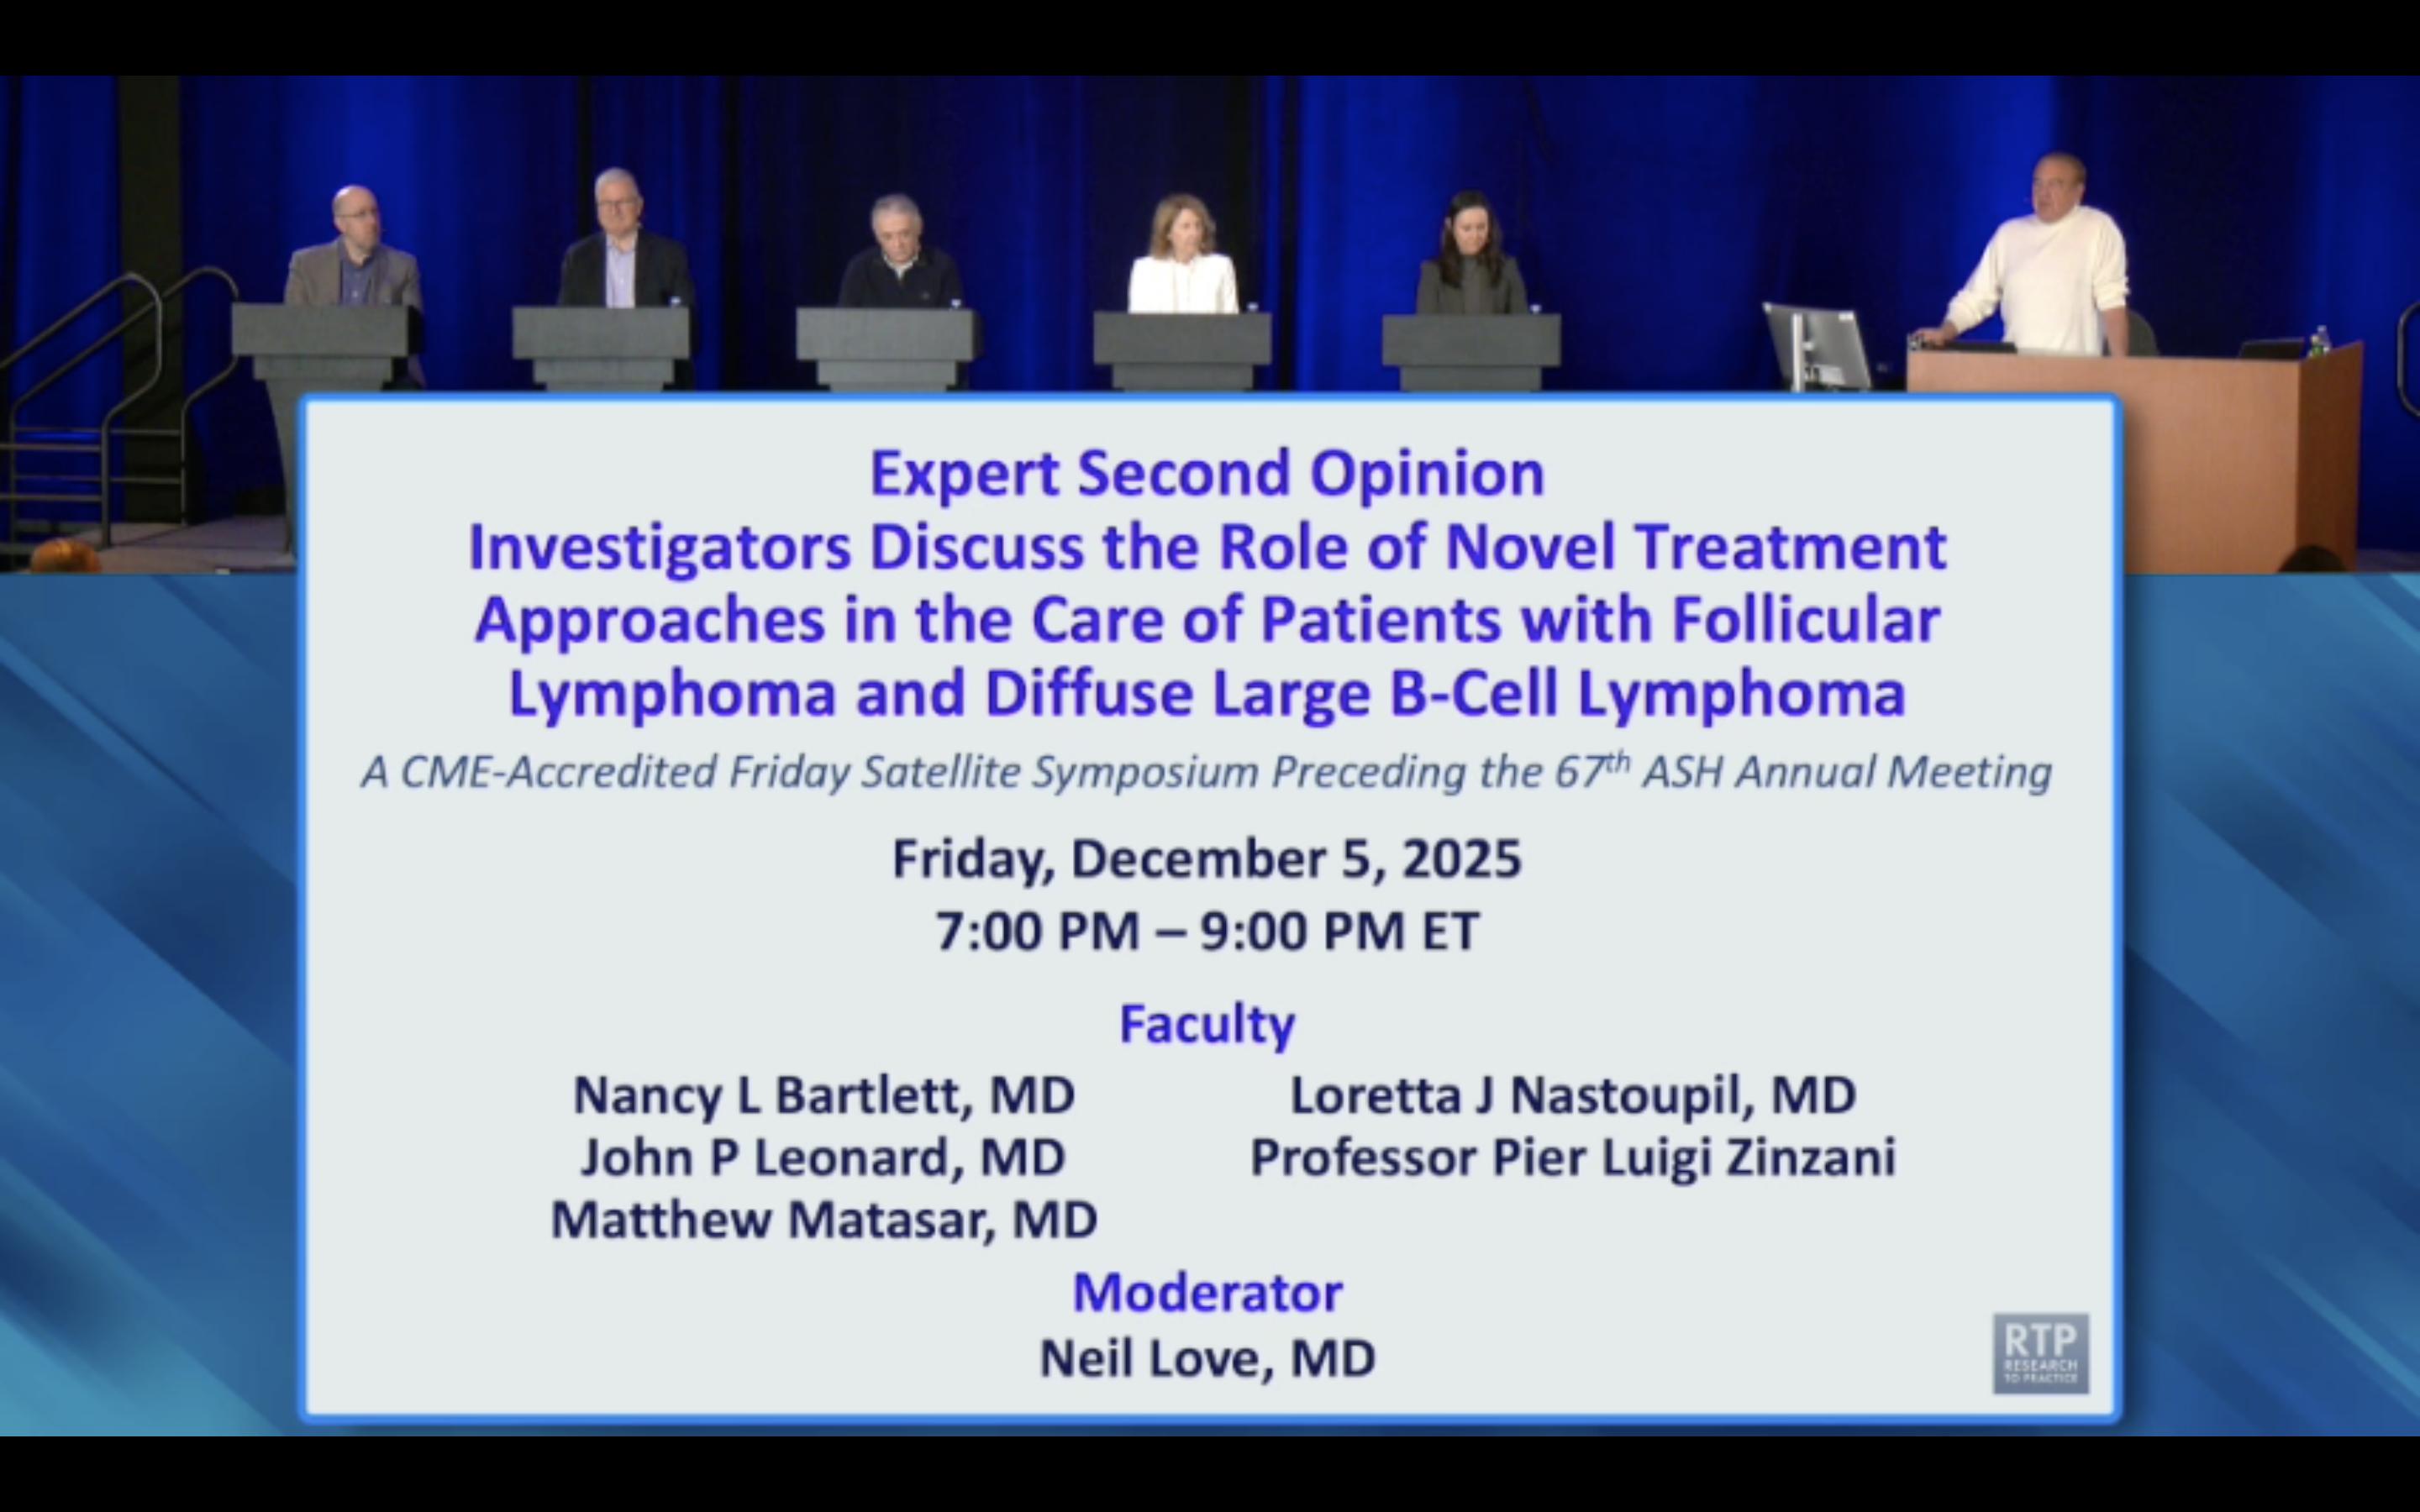
To mitigate the risk of severe Cytokine Release Syndrome (CRS) from bispecific antibodies in patients with high tumor burden, a debulking strategy is effective. Administering two initial cycles of chemotherapy dramatically reduces disease volume, leading to almost zero CRS when the bispecific is introduced, making the treatment much safer.
Data from the MAJESTIC three trial shows bispecific antibodies achieving progression-free survival rates comparable to CAR-T therapy. This creates a new clinical dilemma, forcing a choice between an immediate, off-the-shelf option for rapid progression versus a one-time therapy with a longer track record, making treatment an individualized decision.

Bispecific antibodies are "off-the-shelf" therapies with manageable side effects that don't require specialized manufacturing centers like CAR T. This allows community practices to administer highly effective T-cell redirecting therapies, equalizing access for patients far from major academic institutions.

An expert treating DLBCL states they no longer use bispecific antibodies as monotherapy. Combining them with partners like chemotherapy (GemOx) or ADCs (Polatuzumab) raises the complete response rate by 15-20%, offering a better chance of benefit for patients.

Early trial data for single-agent bispecific antibodies in elderly or frail patients with large cell lymphoma reveals surprisingly high efficacy. This success is prompting discussions about a chemotherapy-free future for this population, with combinations like glofitumab-polatuzumab potentially replacing traditional regimens.
When choosing between BCMA-directed therapies, using CAR-T therapy first may be strategically advantageous. Early evidence suggests continuous T-cell engager (bispecific) therapy may exert more selective pressure, leading to a higher risk of BCMA target loss through mutation or deletion compared to one-time CAR-T infusions.

Moving CAR T-cell therapy from the third-line to the second-line setting for high-risk DLBCL doesn't just improve survival curves, it meaningfully increases the cure fraction from approximately 40% to 50-55%. This quantifiable benefit provides a strong rationale for using CAR T therapy earlier in the disease course.
